

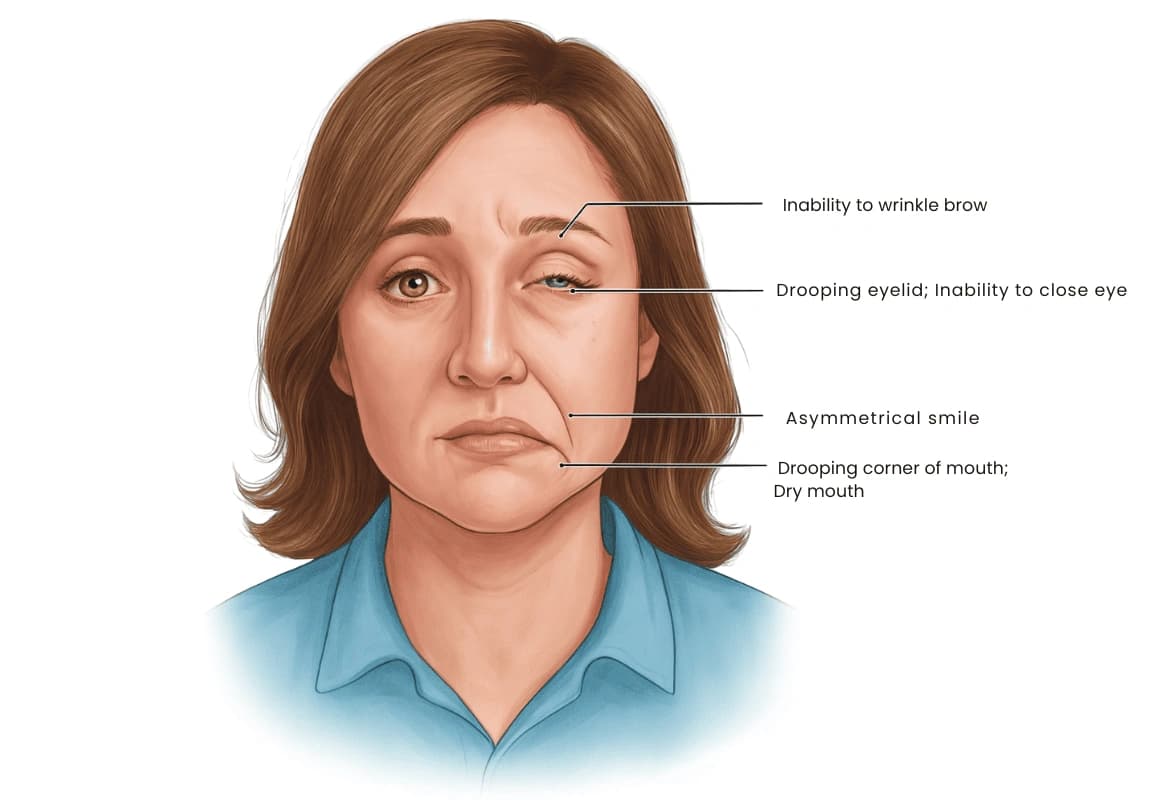
Facial paralysis is a condition where you lose the ability to move some or all of the muscles on one or both sides of your face due to nerve damage or dysfunction. While it can result from various conditions ranging from viral infections like Bell’s palsy to more serious issues such as strokes or tumors, most cases are temporary and treatable when diagnosed early. Understanding the warning signs and underlying causes is crucial for prompt medical intervention and better outcomes.
If you’ve ever woken up to find one side of your face drooping, struggled to close an eye completely, or noticed difficulty smiling evenly, you’ve experienced symptoms that warrant immediate medical attention.
Facial paralysis occurs when the facial nerve (the seventh cranial nerve) becomes damaged, compressed, or inflamed, resulting in weakness or complete loss of movement in the facial muscles. This nerve controls most of the muscles responsible for facial expressions, tear production, and even some aspects of taste and hearing.
The condition can affect people of all ages, though certain causes are more common in specific age groups. The severity can range from mild weakness to complete paralysis, and it may be temporary or permanent depending on the underlying cause.
Understanding what causes facial paralysis is essential for proper diagnosis and treatment. The causes vary widely, from relatively benign viral infections to serious medical emergencies.
Bell’s palsy is the most common cause of sudden facial nerve paralysis, accounting for approximately 60-75% of cases. While the exact mechanism isn’t fully understood, researchers believe viral infections—particularly herpes simplex virus—trigger inflammation that compresses the facial nerve within its bony canal.
This condition typically develops rapidly over 48 hours and can affect anyone, though it’s slightly more common in pregnant women and people with diabetes.
A stroke represents a medical emergency and is among the most serious facial paralysis causes in adults. Unlike Bell’s palsy, which affects the entire side of the face, stroke-related facial weakness typically spares the forehead muscles because they receive nerve signals from both sides of the brain.
Facial paralysis stroke symptoms include:
A tumor causing facial paralysis is less common but requires serious medical attention. Both benign and malignant tumors can compress or invade the facial nerve pathway, leading to progressive weakness.
Acoustic neuromas (benign tumors of the hearing and balance nerve) are the most common benign tumors affecting facial nerve function. These typically cause gradual onset of symptoms including hearing loss, tinnitus, and eventually facial weakness.
Malignant tumors such as parotid gland cancers, temporal bone cancers, or metastatic disease can also affect the facial nerve and usually present with more rapid progression.
Several infections can damage the facial nerve:
Physical trauma represents another significant cause:
Can diabetes cause facial paralysis? Yes, diabetes increases the risk of Bell’s palsy by approximately 29% compared to non-diabetics. The exact mechanism involves damage to small blood vessels that supply the facial nerve, similar to other diabetic neuropathies.
Other systemic conditions include:
While facial paralysis caused by stress isn’t a direct cause-and-effect relationship, chronic stress may contribute to conditions like Bell’s palsy. Stress weakens the immune system, potentially allowing dormant viruses to reactivate and trigger nerve inflammation.
Research suggests that physical or emotional stress in the weeks preceding symptom onset may be a contributing factor in some cases of Bell’s palsy.
Early recognition of facial paralysis symptoms is crucial for timely treatment and better outcomes. The symptoms can vary depending on the severity and underlying cause.
Partial facial paralysis may produce milder symptoms than complete paralysis. Partial weakness might manifest as:
Complete paralysis results in total loss of movement on the affected side.
Facial nerve paralysis symptoms typically include:
Distinguishing between Bell’s palsy and stroke is critical. Remember the acronym F.A.S.T.:
When you present with facial weakness, your healthcare provider will conduct a thorough evaluation to determine the underlying cause.
Your doctor will assess:
Depending on your presentation, tests may include:
Treatment for facial nerve paralysis depends entirely on the underlying cause and should begin as soon as possible.
Surgery may be necessary for:
Facial exercises and physical therapy can help:
The outlook for facial paralysis varies widely:
Q: Can facial paralysis go away on its own without treatment?
A: It depends on the cause. Bell’s palsy often resolves spontaneously in about 70% of cases within several months, though treatment with corticosteroids significantly improves recovery rates. However, other causes like tumors, stroke, or severe infections require specific medical interventions and will not resolve without proper treatment. Never assume facial paralysis will resolve on its own—always seek medical evaluation to identify the underlying cause.
Q: Is facial paralysis contagious or hereditary?
A: Facial paralysis itself is not contagious or directly hereditary. However, some underlying causes can be infectious (like Lyme disease transmitted through tick bites, though not person-to-person) or have genetic components (such as predisposition to certain autoimmune conditions). Bell’s palsy shows some familial clustering, suggesting possible genetic susceptibility, but there’s no specific “facial paralysis gene” that parents pass to children.
Q: How long does it take to recover from facial paralysis, and will my face return to normal?
A: Recovery time varies dramatically based on the cause and severity. Bell’s palsy patients typically see improvement within 2-3 weeks and complete or near-complete recovery within 3-6 months. Mild cases may resolve in weeks, while severe nerve damage might take a year or longer. Approximately 15-20% of people experience some permanent residual weakness. Factors affecting recovery include age, severity of initial paralysis, presence of complete versus partial paralysis, and how quickly treatment begins.
Q: What’s the difference between facial paralysis affecting one side versus both sides?
A: Unilateral (one-sided) facial paralysis is far more common and typically suggests localized nerve damage from conditions like Bell’s palsy, stroke, or tumors. Bilateral (both-sided) facial paralysis is rare but more concerning, often indicating systemic conditions like Guillain-Barré syndrome, Lyme disease, or sarcoidosis. Bilateral facial weakness requires urgent medical evaluation as it may suggest a more serious underlying condition affecting the entire nervous system.
Q: Are there any permanent complications from facial paralysis even after recovery?
A: Yes, some people experience long-term complications even after muscle function returns. These include synkinesis (involuntary movements, such as the eye closing when smiling), crocodile tear syndrome (tearing while eating), facial contractures or tightness, chronic facial pain or numbness, and persistent changes in taste or hearing. Corneal damage from inadequate eye closure during the paralysis phase can also cause permanent vision problems. Early treatment and proper eye protection during the acute phase help minimize these complications.



