

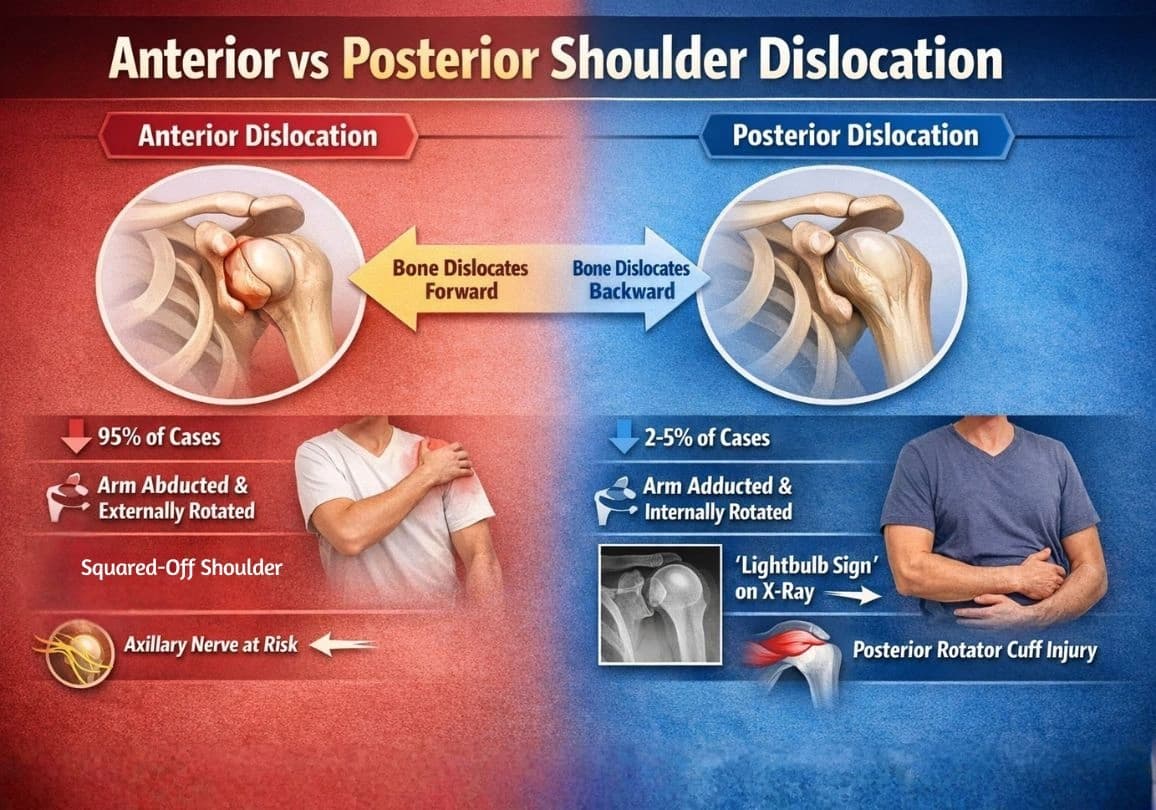
If you’ve ever had a shoulder “pop out,” you know how alarming it feels. But not all shoulder dislocations are the same. When comparing anterior vs posterior shoulder dislocation, the key difference lies in which direction the upper arm bone (humerus) moves out of the socket. In an anterior dislocation, the bone slips forward — and this accounts for nearly 95% of all shoulder dislocations. In a posterior dislocation, the bone shifts backward, which is far rarer but often more difficult to diagnose.
Understanding the difference matters — not just for doctors and physiotherapists, but for anyone who has experienced a shoulder injury and wants to know what’s really going on. At Healyos Physiotherapy, we see both types of dislocations at our Pune clinic and through our at-home physiotherapy services, and early, accurate identification is the first step toward effective recovery.
The shoulder is the most mobile joint in your body — and that mobility comes at a cost. The ball-shaped head of the humerus sits in a shallow cup called the glenoid cavity, held in place by muscles, tendons, and ligaments. When a force is strong enough to push that ball out of the cup, a dislocation occurs.
There are two main directions this can happen:
There are also inferior dislocations (downward), but these are extremely uncommon and beyond the scope of this comparison.
Anterior dislocations typically occur when the arm is in an abducted and externally rotated position — think of falling on an outstretched hand, a tackle in sports, or a direct blow to the back of the shoulder.
When the humeral head slides forward, the shoulder takes on a distinctive “squared-off” appearance. The natural rounded shape of the shoulder disappears, and there may be a visible bulge at the front of the joint.
Classic signs of anterior dislocation:
This is where things get interesting — and where misdiagnosis is most likely. Posterior shoulder dislocation typically results from:
Posterior dislocations are notoriously easy to overlook. On a standard AP (front-facing) X-ray, the joint can appear almost normal to an untrained eye. Studies suggest that up to 50–79% of posterior dislocations are initially missed, sometimes for weeks or months. This is one reason understanding anterior vs posterior shoulder dislocation on X-ray findings is so critical in clinical settings.
The shoulder may appear less dramatically deformed than with an anterior dislocation, which contributes to delayed diagnosis.
Classic signs of posterior dislocation:
This is one of the most clinically important aspects of comparing these two conditions. Anterior vs posterior shoulder dislocation radiology findings can look very different — or surprisingly similar.
On a standard AP view, the diagnosis is usually straightforward:
This is where anterior vs posterior shoulder dislocation on X-ray becomes a real diagnostic challenge:
A Y-view or axillary lateral X-ray is essential to confirm a posterior dislocation. This is why many guidelines now recommend obtaining two views at a minimum whenever a shoulder dislocation is suspected.
Clinical Pearl: If a patient presents with a shoulder injury after a seizure and cannot externally rotate their arm, a posterior dislocation should be suspected until proven otherwise — even if the AP X-ray looks normal.
Regardless of type, the first step is reduction — getting the humeral head back into the socket. This is done by a trained clinician, usually in an emergency setting, often with sedation or analgesia.
Once the shoulder is back in place, the real work begins. A dislocation — whether anterior or posterior — leaves behind damaged soft tissue, weakened muscles, and a joint that’s now at higher risk of dislocating again.
At Healyos Physiotherapy, our post-dislocation rehab program typically includes:
Whether you visit our Pune clinic or prefer the convenience of our at-home physiotherapy service, our team designs a personalised programme based on which type of dislocation you had, your activity level, and your recovery goals.
Yes, and recurrence is actually quite common — especially after an anterior dislocation in younger, active individuals. Studies show that recurrence rates can be as high as 50–90% in people under 25 who return to sport without proper rehabilitation. This is why structured physiotherapy, aimed at strengthening the rotator cuff and restoring joint stability, is so important. If recurrence is frequent, surgical options like a Bankart repair may be recommended.
Recovery time varies depending on the type of dislocation, how severe the soft tissue damage is, and whether there are associated fractures. In general, most people can return to light daily activities within 2–4 weeks. A return to sports or heavy lifting typically takes 3–6 months. Posterior dislocations, especially if missed early, may take longer to recover due to the complexity of the injury.
Not necessarily. Most first-time dislocations are managed conservatively — reduction followed by physiotherapy. However, surgery may be recommended in cases of recurrent dislocation, significant bone loss (like a large Hill-Sachs or Bankart lesion), associated fractures, or when conservative treatment fails over multiple attempts. A specialist assessment is always recommended.
Unfortunately, yes. This is a well-documented clinical problem. Because a posterior dislocation may not show clearly on a standard front-view X-ray, and because the shoulder deformity can be subtle, it is frequently misdiagnosed as a frozen shoulder, shoulder strain, or another condition. If you had a seizure or electric shock and your shoulder hasn’t been right since, ask your doctor specifically about the possibility of a posterior dislocation.
In the first 48–72 hours after a dislocation or reduction, ice is generally recommended. It helps manage pain and reduce swelling. Apply for 15–20 minutes at a time with a cloth barrier to protect the skin. Heat may be introduced later in the rehabilitation phase (after acute swelling has settled) to help with muscle relaxation before exercises. Your physiotherapist will guide you on when to make the switch.



